Medical Expertise at Luxe Aesthetic Surgery
Luxe Aesthetic Surgery & Medical Spa is led by Haimesh Shah, MD, RPVI , a physician specializing in cosmetic surgery, body contouring, laser procedures, and venous medicine. Dr. Shah is a Diplomate of the American Board of Laser Surgery, American Board of Venous & Lymphatic Medicine, American Board of Wound Management, and American Board of Internal Medicine. He also holds the Registered Physician in Vascular Interpretation (RPVI) credential and has contributed to peer-reviewed medical research.
Would surgery address the cause of a man's chest fullness, or only its appearance? Gynecomastia surgery removes excess fat, firm glandular tissue, loose skin, or a combination, depending on what is contributing to the enlargement. Before planning an incision, a clinician should assess whether a reversible cause, such as a medication or hormone shift, may be involved.
A soft layer of fat and a firm disc beneath the nipple can look similar through clothing, but they may call for different approaches. Loose skin is another factor. The right plan starts by identifying which tissue is present.
Say a man in his thirties develops a puffy nipple after starting a new prescription and gaining 15 pounds. Liposuction may not remove firm glandular tissue, and surgery before reviewing the medication could address fullness that might improve once a reversible trigger is managed. The tissue and its possible cause both matter before an operation is chosen.
Table of Contents
- What Gynecomastia Surgery Removes and Why It Matters
- Causes of Male Breast Enlargement and How They Are Evaluated
- Liposuction, Excision and Combined Techniques Compared
- Awake Surgery Versus General Anesthesia
- Who Is a Good Candidate and When to See a Specialist
- Recovery Timeline and Realistic Results
- Complications to Discuss Before You Book Surgery
- Book a Consultation to Confirm Your Surgical Plan
What Gynecomastia Surgery Removes and Why It Matters
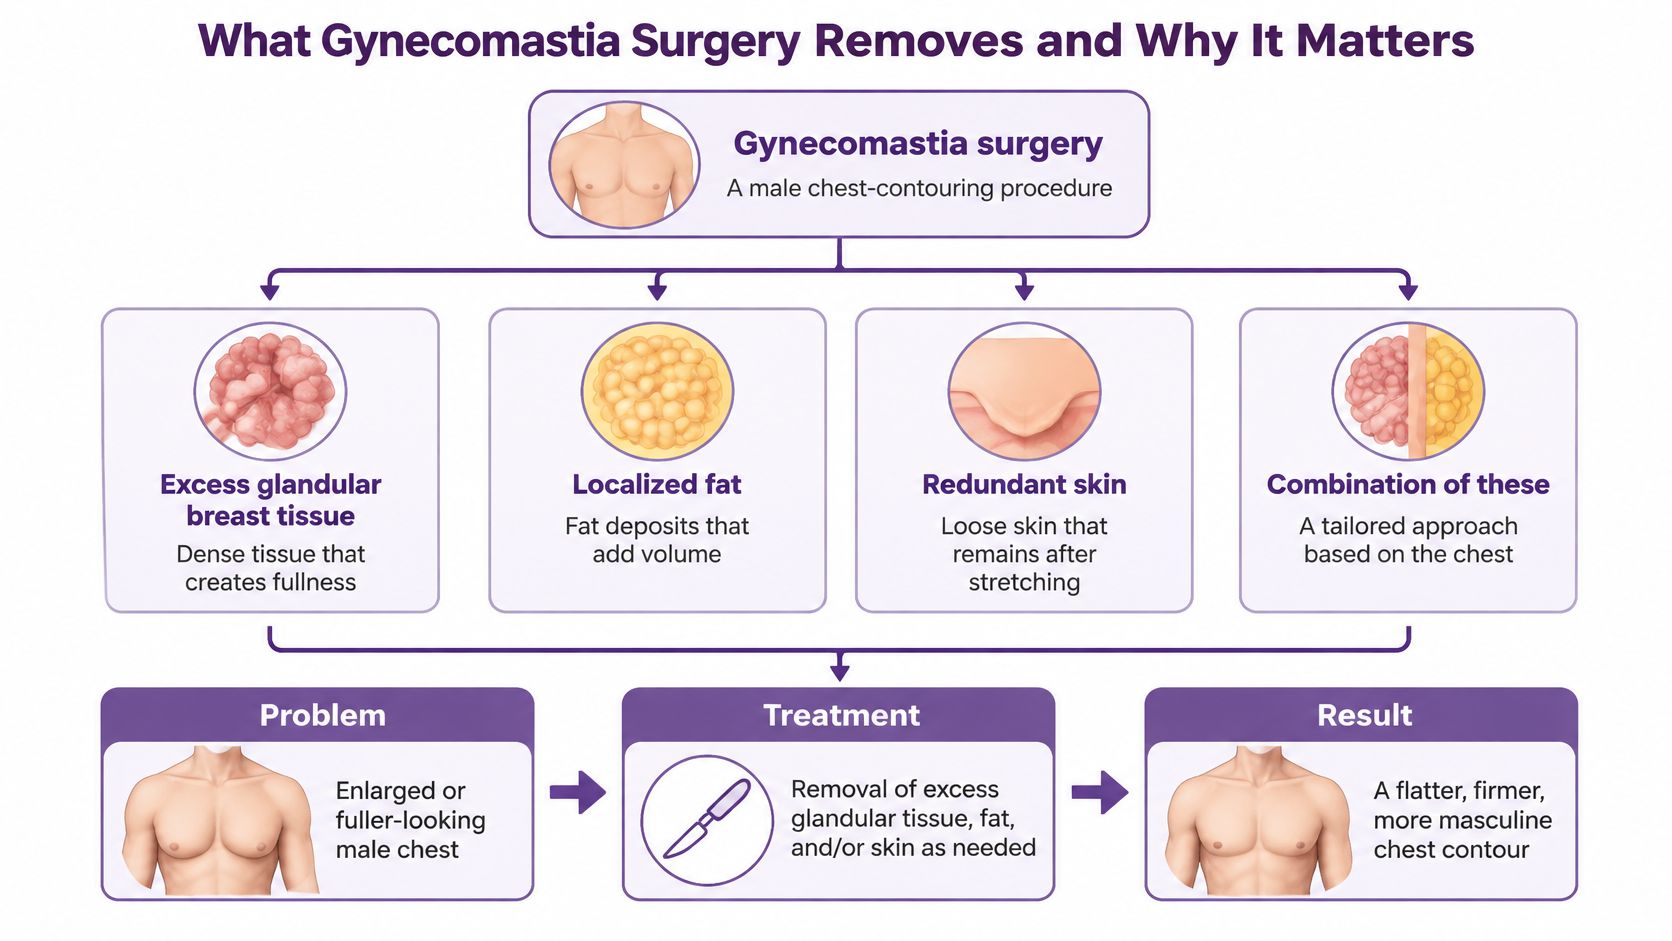
What tissue is creating the chest fullness? Gynecomastia surgery can remove excess glandular breast tissue, localized fat, redundant skin, or a combination of them. A surgical review estimates that the condition affects up to 65% of men at some point, although many cases are mild and do not require surgery.
Fat feels soft and spreads across the chest. Gland tissue is firmer and often forms a disc beneath the nipple, while loose skin may remain after the chest loses volume. Liposuction is used for fatty tissue; firm gland often requires direct excision. When both are present, surgeons may combine the techniques. The same review, covering 1,112 surgically treated patients, found skin-sparing mastectomy, with or without liposuction, was the most frequently used approach. The operation is adapted to the tissue and its distribution.
Power-assisted and ultrasound-assisted liposuction, as well as endoscopic approaches, are designed to limit the incisions or scar burden. A smaller access point still cannot remove dense gland tissue by suction alone.
Before planning an incision, the surgeon also considers whether a reversible cause of enlargement is still active. The procedure reshapes the chest, while its contour depends on more than the amount of tissue removed. Nipple position, skin quality, asymmetry, and a gradual transition across the chest all help determine the plan.
Causes of Male Breast Enlargement and How They Are Evaluated
What is causing the chest fullness: fat, glandular tissue, or a change that may improve when its trigger is addressed? That distinction shapes the evaluation and helps determine whether surgery is appropriate.
Medications are among the possible contributors. Prescription and nonprescription drugs can be linked to breast tissue growth. Anabolic steroids, alcohol, and other substances may also affect hormone signaling or how the liver handles hormones. Thyroid, liver, kidney, or other hormonal disorders can contribute too, and treating the underlying problem may reduce enlargement.
Weight gain can add fat to the chest without forming a firm glandular disc beneath the nipple. Puberty is another common context for temporary enlargement, which often improves on its own.
For recent enlargement or a suspected reversible cause, evaluation comes before an incision plan. Endocrine Society–referenced clinical guidance recommends deferring surgery until the underlying cause has resolved or been treated. The Merck Manual guidance on gynecomastia describes spontaneous improvement in many cases and notes that surgery may be considered after approximately 12 months in appropriate cases. A suspected medication change should be discussed with the prescribing clinician. Do not stop a drug on your own.
How an evaluation usually runs
- History of onset: When the enlargement began, how quickly it changed, and whether one or both sides are affected.
- Medication and substance review: Prescription drugs, supplements, steroids, alcohol, and over-the-counter products all belong in the discussion.
- Chest examination: The clinician assesses firmness, whether there is a central lump or a one-sided mass, and the skin and nipple position.
- Blood tests when indicated: These may be ordered if a hormonal or organ-related cause is suspected. They are not a routine requirement for every mild case.
- Timing decision: Based on the earlier steps, the next choice may be observation, a supervised medication change, or surgery.
A Goodlabs men's hormone panel can help organize testosterone and related markers for discussion with a clinician. If a medication or treatable hormone problem is still active, removing tissue does not remove the trigger, and enlargement may continue while the chest heals.
Liposuction, Excision and Combined Techniques Compared
Which technique fits depends on whether the chest fullness comes mainly from fat, firm glandular tissue, loose skin, or a combination. Fat and gland can overlap, so the plan may use more than one method.
What each method actually takes out
Liposuction removes excess fat through small cannula incisions. Power-assisted and ultrasound-assisted methods change how the cannula works through the fat, but they cannot reliably remove dense gland beneath the nipple. A guide to liposuction techniques and preparation explains how cannula-based fat removal works.
Direct excision, also called subcutaneous mastectomy, removes firm gland through an incision around or across the areola. It can address a rubbery disc beneath the nipple. Removing too much tissue from this area can leave a visible dent.
Combined surgery uses liposuction for fat and limited excision for the gland. The surgeon must preserve a thin layer of tissue beneath the nipple-areola to maintain its blood supply.
Skin reduction may be used when loose skin remains, often after major weight loss. It removes and repositions skin, which means longer scars and a longer recovery than procedures focused on fat or gland alone.
Free nipple-areola grafting is an uncommon option for severe skin laxity with a displaced nipple. The nipple-areola is removed and placed as a graft.
| Technique | Best Fit | Incision and Tissue Removed | Main Trade-Off |
|---|---|---|---|
| Liposuction (power-assisted or ultrasound-assisted) | Mainly fatty enlargement with good skin elasticity | Small cannula incisions; fat only | Cannot reliably remove firm gland |
| Direct excision (subcutaneous mastectomy) | Firm glandular tissue | Periareolar or transareolar incision; gland removed | Risk of contour irregularity or visible scarring |
| Combined liposuction and excision | Both fat and gland present | Cannula incisions plus periareolar incision | More complex; nipple-areola blood supply must be preserved |
| Skin reduction | Excess skin, often after major weight loss | Skin excision around the areola or chest | Longer scars and a longer recovery |
| Free nipple-areola graft | Severe skin laxity with a displaced nipple | Nipple-areola removed and regrafted | Most involved option; rarely needed |
The aim is a smooth chest contour, a suitable nipple-areola position, and enough tissue beneath the nipple to avoid a scooped-out appearance. The right balance depends on the tissue present and the surgeon's assessment of the skin and chest shape.
For example, suction alone may leave fullness if firm gland is still beneath the nipple. Excision alone may not address excess fat across the chest. When both are present, combining the techniques can treat each tissue type while protecting the tissue that supports the nipple.
Awake Surgery Versus General Anesthesia
Anesthesia is a separate decision from which tissue comes out. Two broad approaches cover most gynecomastia operations, and they aren't interchangeable for every patient.
General anesthesia uses IV medication so you're fully asleep, with a breathing tube or another airway device and continuous monitoring. It's often chosen when the operation is longer, when skin excision is extensive, or when medical history makes a lighter plan a poor fit.
Local anesthesia with sedation numbs the surgical area while medication keeps you comfortable. For liposuction, surgeons often infuse tumescent solution into the fat first. That fluid carries anesthetic and helps limit bleeding in the suctioned layer. You aren't having a pain-free guarantee. You're having a numbed field and a plan for comfort, and some pressure or awareness can still occur.
Whether a given gynecomastia operation can be done this way depends on the technique, how much surgery is planned, your medical history, and the surgeon's assessment. Not every chest operation is done the same way. Luxe Aesthetic Surgery & Medical Spa performs certain body-contouring procedures under local anesthesia. Whether gynecomastia surgery can be performed awake for you is decided at consultation, based on anatomy and medical history. Tumescent local anesthesia is one setting where that local approach is used for appropriate candidates.
Local anesthesia isn't always safer. General anesthesia isn't dangerous by definition. Both carry risks, including bleeding, drug reactions, breathing problems, and incomplete comfort that can force a change in plan. "Awake" doesn't mean zero downtime, and it doesn't mean every patient qualifies.
Questions worth asking before you book
- Which anesthesia is proposed, and why this chest needs it? Tie the answer to gland versus fat and to how much skin work is planned.
- Who administers it, and what monitoring is used? You want a named person and a clear monitoring plan, not a vague "you'll be comfortable."
- What happens if the plan has to change during surgery? Ask how you'd be deepened or converted, and who makes that call.
Who Is a Good Candidate and When to See a Specialist
Surgery corrects established anatomy. It doesn't erase a hormonal, medication, weight, or systemic driver. A typical candidate is an adult with enlargement that has already persisted, plus pain, functional discomfort, or real psychosocial distress. Stable weight, no active drug or substance change still driving the chest, realistic expectations, and no medical problem that makes surgery unsafe all belong on that list.
Adolescents are different. Published reviews commonly recommend observation for at least 12 months when that's clinically appropriate, because spontaneous resolution may occur, as noted in a review of surgical candidacy and risk. Timing is individualized. Age alone isn't a green light.
Delay the operation when onset is recent, a medication or hormone issue hasn't been evaluated, growth is rapid, or weight is changing for reasons you can't explain. Those are reasons to pause, not reasons to ignore the chest.
Findings that need medical evaluation first
These aren't cosmetic planning items. They need prompt assessment to rule out other causes before any discussion of contour surgery.
- A single firm lump on one side. A discrete unilateral mass is examined, not assumed to be ordinary gynecomastia.
- Nipple discharge. Fluid from the nipple changes the workup.
- Bleeding from the nipple. That's a medical finding, not a scar question.
- Skin changes over the lump. Color, texture, or fixation to skin needs a clinician's eyes.
- Pain that's new or worsening. New pain isn't the same as long-standing tenderness.
Before surgery, the assessment reviews medications and medical conditions, looks for a one-sided mass or other concerning findings, and sorts the correction into fat-dominant, gland-dominant, or skin-dominant. Under-resection can leave a persistent subareolar mass. Over-resection under the nipple can produce a visible saucer deformity. The surgeon has to leave a thin vascularized soft-tissue layer, not chase a perfectly empty space.
Recovery Timeline and Realistic Results
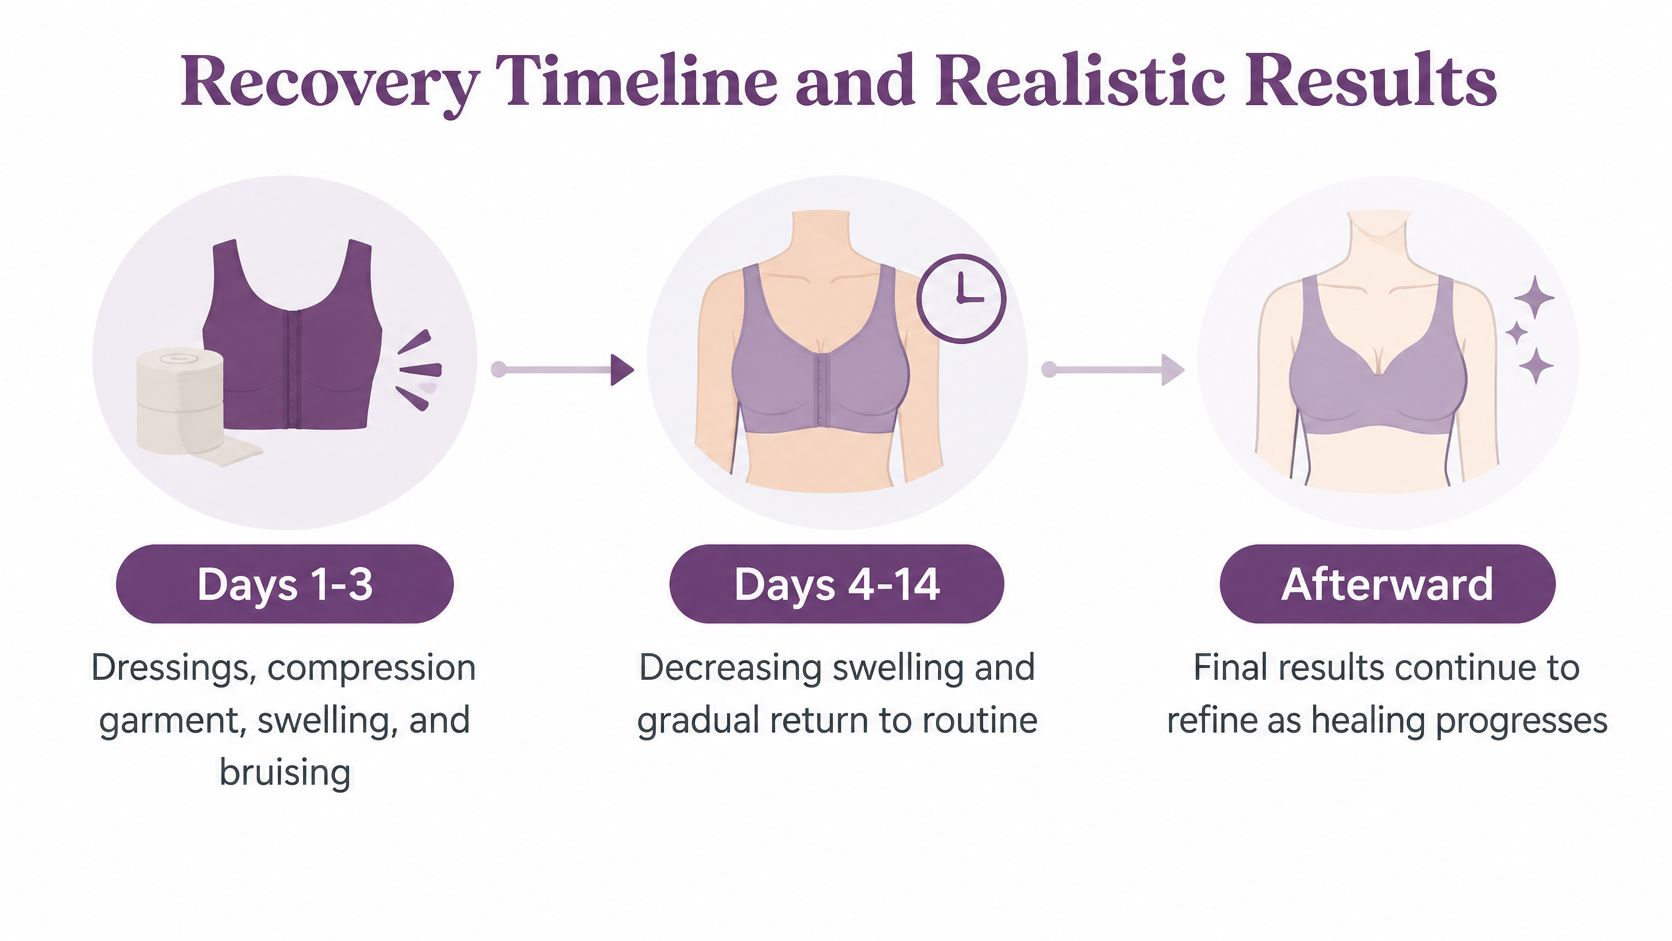
How soon can you return to normal after gynecomastia surgery? Recovery is gradual: swelling and bruising are expected at first, while light daily activity usually resumes before strenuous exercise. Dressings and a compression garment support the early healing period. The timing depends on the technique, the amount of tissue removed, and your healing, so your surgeon's instructions set the pace.
| Phase | Typical Timing | What to Expect | What to Do |
|---|---|---|---|
| Early recovery | First 1-3 days | Dressings, compression garment, swelling and bruising | Rest and follow written instructions |
| Initial healing | Days 4-14 | Swelling decreasing; return to light daily activity | Avoid strenuous exercise until cleared |
| Settling | Weeks 3-6 | Residual swelling; sensation changes possible | Attend follow-up visits |
| Final contour | Months 3-12 | Shape continues to refine as swelling resolves | Confirm final-result timing with the surgeon |
If your procedure includes chest liposuction, garment use, walking, and avoiding early chest workouts follow the same general principles as recovery after liposuction. Gland excision or skin removal may add wound care and extend lifting restrictions. Follow your own surgeon's timeline rather than comparing your recovery with someone else's.
The goal is a better chest contour, with the final shape becoming clearer as swelling settles. It can take months to see the result. A 2025 study of proactive fat grafting found no statistically significant difference in aesthetic satisfaction after a mean 12.4-month follow-up, as reported in a 2025 fat grafting study.
Three look-alikes that aren't the same problem
Recurrence or renewed enlargement. Surgery does not prevent new growth if a continuing cause remains. Hormonal imbalance, medications, anabolic steroids, obesity, and liver or kidney disease can contribute to renewed enlargement.
Later fat gain. Weight gain can add fat to the chest even after gland tissue has been removed. That change reflects a new fat layer, not necessarily renewed gland growth.
Ordinary postoperative swelling is another temporary change. It should be interpreted in the context of the recovery timeline and your surgeon's follow-up assessment.
Complications to Discuss Before You Book Surgery
Complication risk varies with the technique and the tissue being treated. A systematic review of studies published from January 1, 1987, through November 1, 2020, reported complications in 14.87% of patients treated with aspiration techniques, 30.64% after surgical excision, and 11.76% after combined techniques, according to the systematic review in Aesthetic Plastic Surgery. These figures come from different studies and should not be treated as a personal forecast. The range of possible outcomes is one reason to ask how the planned operation fits your anatomy.
A review of 1,112 patients found that major-complication rates varied widely, from 0% to 33%. Hematoma, a collection of blood beneath the skin, was the most common major complication at 5.8%; seroma, a pocket of fluid, occurred in 2.4%. Procedure-specific reports also varied: hematoma rates were as low as 1% after liposuction alone or liposuction with an arthroscopic shaver for mild cases, compared with 11% to 16% after open subcutaneous mastectomy. Combining liposuction with limited gland excision can address both fatty and firm tissue, but it does not eliminate risk.
A 2024 series using tumescent local anesthesia, liposuction, and periareolar excision reported major postoperative complications in 6.7% of patients: three hematomas and one seroma. Minor complications occurred in 5%, including two nipple-areola retractions and one recurrence that required another combined procedure. In a 2025 comparison of 32 breasts, the liposuction-only group had bruising and two hematomas, including one revision for persistent puffy nipples. The excision group had four crater deformities, one case of superficial skin necrosis, one hematoma, and one seroma.
| Complication | Reported Frequency | What It Means | Typical Management |
|---|---|---|---|
| Hematoma | 5.8% of major complications in a review of 1,112 patients; procedure-specific reports ranged from 1% to 11%–16% | Blood collection under the skin | Drainage or evacuation if needed |
| Seroma | 2.4% in the same review | Fluid collection after surgery | Aspiration or temporary drain |
| Infection | Included in overall complication estimates; no single isolated rate is given here | Bacterial infection of the surgical site | Antibiotics and drainage when indicated |
| Contour irregularity or saucer deformity | Four crater deformities in the excision group in a 2025 comparison of 32 breasts | Uneven chest surface or visible flattening under the nipple | Revision surgery in selected cases |
| Nipple or areola changes | Two nipple-areola retractions in a 2024 series using tumescent liposuction and periareolar excision | Numbness, flattening, retraction, or compromised nipple blood supply | Monitoring; revision in selected cases |
| Asymmetry or residual tissue | Recognized after under-resection or uneven healing; no pooled percentage is given here | Sides differ, or a persistent subareolar mass remains | Revision surgery in selected cases |
Informed consent should cover bleeding or hematoma, infection, seroma, asymmetry, contour changes, altered sensation, scarring, nipple-areola problems, and possible revision. Ask which risks apply to your planned technique, what the surgeon would do if a hematoma develops in the first days, and how a persistent puffy nipple or crater would be addressed after swelling has subsided.
Book a Consultation to Confirm Your Surgical Plan
What is causing the chest fullness, and could a reversible cause be contributing? Those answers should come before choosing an operation. Fat, glandular tissue, loose skin, or a combination each calls for a different plan.
Bring a list of current medications and supplements, any hormone or thyroid test results, a timeline of when the chest changed, your weight history, and written questions about anesthesia and recovery. Ask what the surgeon expects the result to look like at a year. These details help connect the exam findings to a specific surgical approach.
Luxe Aesthetic Surgery & Medical Spa serves patients in Southern California. Treatment planning is individualized around anatomy, goals, and lifestyle. Medical Director Haimesh Shah, MD, RPVI, holds board certifications from the American Board of Venous and Lymphatic Medicine, the American Board of Laser Surgery, and the American Board of Internal Medicine. If a concerning finding is present, have it evaluated before requesting surgery. Otherwise, request a consultation through luxeaestheticsurgery.com to discuss a plan based on your tissue and exam.
Luxe Aesthetic Surgery & Medical Spa offers gynecomastia surgery for chest fullness caused by fat, glandular tissue, loose skin, or a combination. The technique and anesthesia are determined after an exam. If you're in Southern California, visit Luxe Aesthetic Surgery & Medical Spa to request a consultation.